



 Inglês (pdf)
 Artigo em XML
 Referências do artigo

 Tradução automática
 Enviar este artigo por email
 Citado por SciELO
 Similares em
SciELO

 Permalink

INTRODUCTION
The Amazon, renowned for its remarkable biological and sociocultural diversity, presents unique challenges to medical practice, from geographic and logistical barriers to the complex interplay between traditional knowledge and scientific medicine. Working in Amazonian communities requires physicians not only to master technical skills but also to demonstrate intercultural sensitivity, creativity in the face of scarce resources, and a profound sense of social responsibility1.
Riverine and Indigenous populations live in conditions of pronounced vulnerability, facing severe limitations in access to healthcare, sanitation, adequate nutrition, and education. In this context, health professionals are frequently required to assume multiple roles, ranging from clinical care to health education and cultural mediation. Nevertheless, Brazilian medical training remains largely centered on urban, hospital-based environments, with limited exposure to peripheral and remote realities2,3.
Beyond logistical and social barriers, the Amazonian setting is deeply marked by socio-environmental vulnerabilities. Deficient sanitation, limited access to safe drinking water, and food insecurity coexist with environmental threats such as illegal mining, deforestation, and climate change4. Extreme weather events, including the historic drought of 2024, which left numerous communities isolated for weeks, illustrate how ecological imbalances directly affect daily life and health outcomes4. These circumstances increase the complexity of medical work and underscore the urgent need for professionals capable of integrating environmental determinants into healthcare practice.
Against this backdrop, field-based initiatives such as volunteer missions in Amazonian territories have gained prominence by providing immersive practical experiences that foster interpersonal competencies, empathy, resilience, and a critical understanding of health inequities5,6,7. Despite their growing relevance, few studies have systematically examined the educational impact of these experiences from the students' perspective. Understanding how such immersions influence learning processes and professional identity can inform curricular improvement and strengthen educational practices committed to health equity8.
Accordingly, this study analyzes the experiences of medical students who participated in the Amazon Volunteer Mission, identifying the main challenges encountered, lessons learned, and the effects of this experience on their academic and personal development.
MATERIALS AND METHODS
This qualitative, exploratory, multi-method study was conducted within Morin's paradigm of complexity, which integrates the dialogical, recursive, and hologrammatic principles9. Three complementary phases were carried out.
PHASE 1 - LITERATURE REVIEW
A narrative review mapped the main challenges faced by health professionals in the Amazon and identified theoretical gaps in medical training within socio-environmentally vulnerable contexts. The findings guided the construction of the interview script.
PHASE 2 - PRIMARY DATA COLLECTION
Semi-structured interviews were conducted online with a purposive sample of ten medical students who had participated in volunteer missions in Amazonian riverside communities during 2023 or 2024. Inclusion criteria were documented participation in the mission and signed informed consent. Exclusion criteria included failure to provide consent, incomplete questionnaires, incoherent responses, direct personal ties to the researchers, or emotional discomfort leading to withdrawal.
The missions were carried out in communities located between Manacapuru and Canabuoca, in the state of Amazonas, with transportation occurring primarily by river. The main activity sites were approximately 100 km apart (Figure 1).
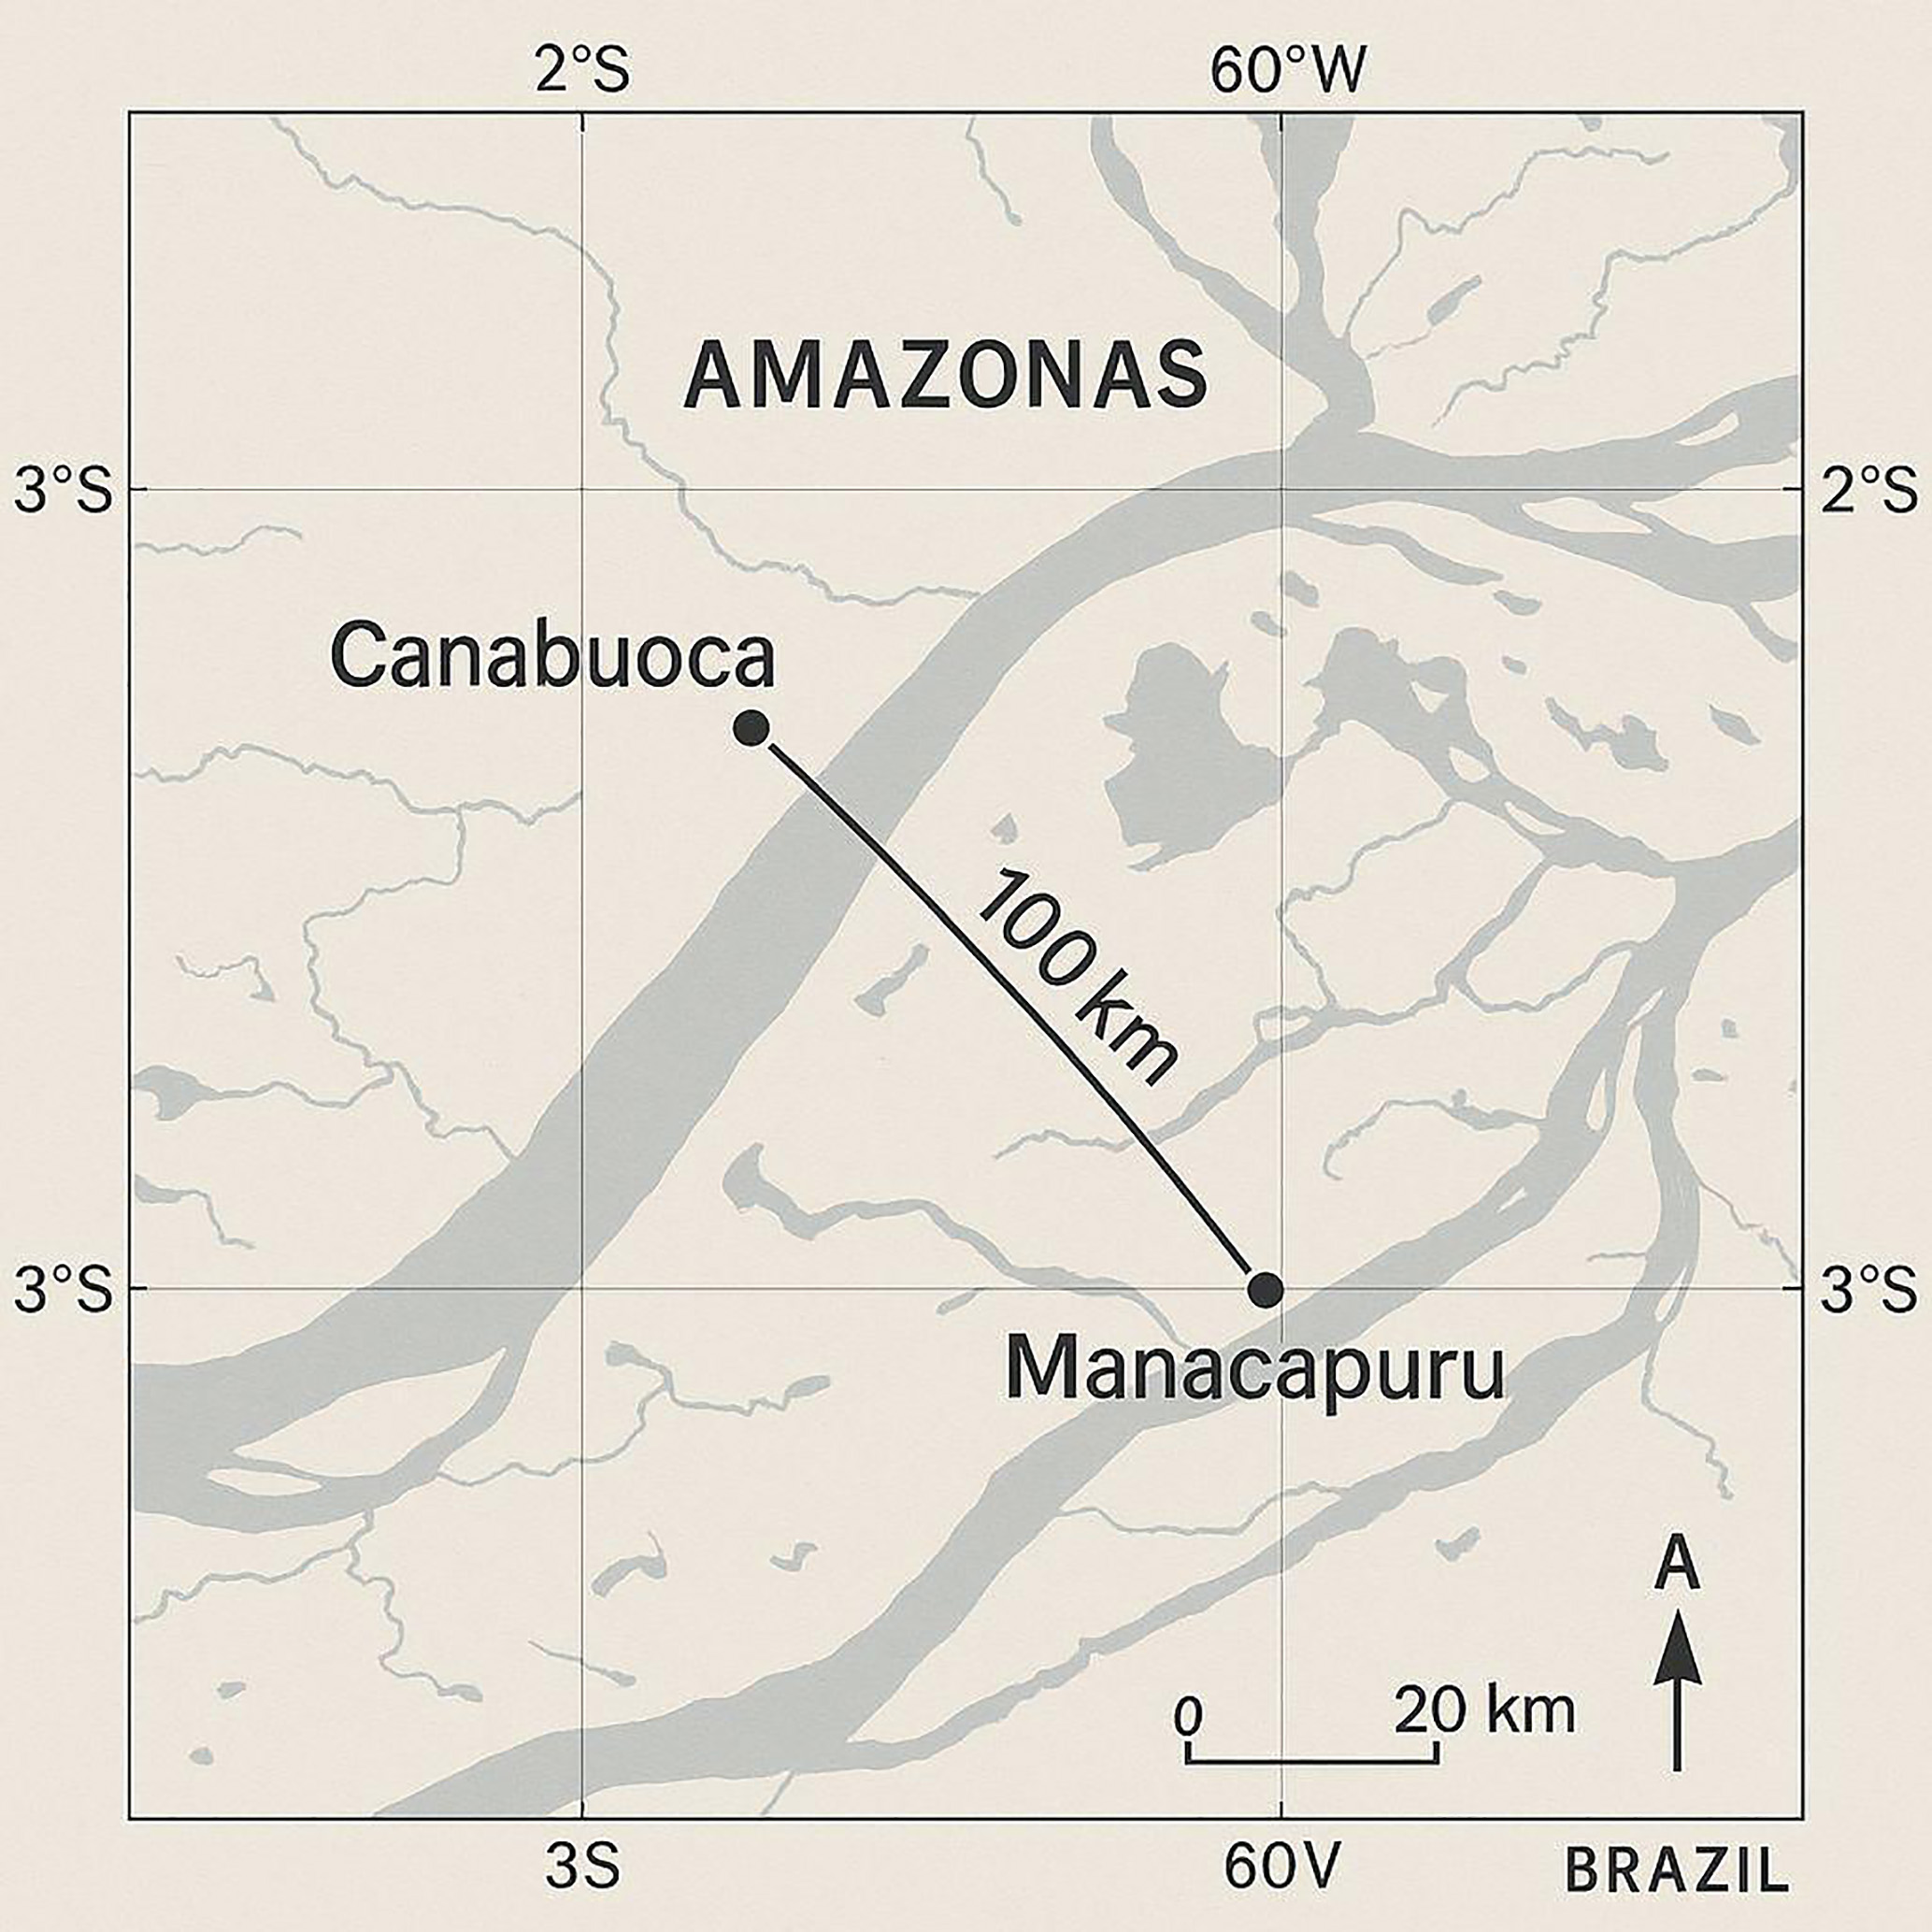
Figure 1 - Map of the operational area of the Amazon Volunteer Mission, highlighting the communities served by the medical students
The region is characterized by difficult access and high social vulnerability, marked by long boat journeys, limited basic services, and environmental constraints imposed by seasonal flooding and drought. The community of Canabuoca, in particular, has approximately 400 inhabitants, most of whom are descendants of Indigenous peoples. Fishing is the primary economic activity, complemented by subsistence agriculture, especially corn cultivation. Houses are built of wood on stilts, allowing adaptation to the seasonal rise of the Solimões River, when transportation is only possible by boat.
Sanitation conditions are precarious: there is no sewage system or regular waste collection, and the water consumed is taken directly from the river, typically boiled or treated with chlorine drops before drinking. Electricity is supplied by community generators that operate intermittently. There is no permanent health post, and according to residents, the mission analyzed in this study was the first to provide structured medical care in the locality. In case of health emergencies, inhabitants must travel to Manaus, an eight-hour boat trip followed by an additional hour by car, with costs often unaffordable for local families.
Manacapuru, which serves as a reference point for some riverside communities, has a Municipal Human Development Index (MHDI) of 0.657, reflecting persistent social inequalities. Although the city has a broader network of health services, riverside and traditional populations living on its margins still face barriers to continuous care, including logistical and financial constraints.
The interview instrument included six sociodemographic items (age, sex, marital status, self-reported skin color, semester, and place of origin) and five open-ended questions about the individual experience:
PHASE 3 - DATA ANALYSIS AND INTEGRATION
Interview transcripts were subjected to Bardin's content analysis10, which generated thematic categories later triangulated with the literature to produce an expanded understanding of the educational impacts.
LITERATURE REVIEW
Brazilian medical education has been criticized for its excessive focus on urban, hospital-based contexts that inadequately reflect the realities faced by much of the population. In response, service-based learning, experiential education, and the humanization of care have gained increasing importance in national curricular guidelines5.
EXPERIENTIAL AND SERVICE-BASED LEARNING
Experiential learning, rooted in the integration of theory and practice, is a cornerstone for developing clinical, social, and emotional competencies. Walters et al.11 argue that immersive experiences in challenging settings, such as Amazonian missions, foster reflective and critical practice while broadening students' understanding of the social role of medicine. These experiences expose students to the social determinants of health, resource scarcity, and interprofessional teamwork. Service-based learning further connects students to real community needs, embedding values of solidarity, empathy, and social justice into medical education12.
DEVELOPING RESILIENCE IN CHALLENGING ENVIRONMENTS
Working in vulnerable territories such as the riverine Amazon demands not only technical proficiency but also emotional capacities, including resilience, adaptability, and tolerance for frustration. Exposure to adversity during training enhances coping abilities and prepares students to face uncertainty in real-world practice6. Such field experiences reinforce the concept of expanded competence, in which medical Knowledge interweaves with ethical, relational, communicative, and cultural dimensions.
HUMANIZATION OF MEDICINE AND EMPATHY
Humanized medical practice, closely associated with empathy and effective communication, is a key focus of Brazil's national curriculum guidelines. Empathy, defined as the ability to understand and share another person's experience, has been linked to improved treatment adherence, patient satisfaction, and clinical outcomes13. Yuguero et al.7 demonstrated an inverse association between empathy and burnout among primary care professionals, while Junior et al.8 showed that empathy can be cultivated and strengthened through exposure to real-world healthcare contexts, particularly in vulnerable settings. Volunteer missions in the Amazon therefore expand students' clinical repertoire and promote deep reflection on human dignity, active listening, and person-centered care.
RESULTS
The sample comprised ten medical students who participated in the Amazon Volunteer Mission during 2023 and 2024. Most participants were female (70%) and aged between 22 and 26 years. All were regularly enrolled between the seventh and twelfth semesters of the program and reported no prior experience in riverside regions. All participants came from urban areas, with limited or no previous involvement in volunteer work, which amplified the contrast between their academic background and the Amazonian context. Table 1 presents the absolute and relative frequencies of the students' sociodemographic characteristics.
Table 1 - Sociodemographic characteristics of medical students participating in the Amazon Volunteer Mission
| Variable | Category | n | % |
|---|---|---|---|
| Age (years) | 20-25 | 6 | 60 |
| 26-29 | 3 | 30 | |
| 30-35 | 1 | 10 | |
| Sex | Male | 3 | 30 |
| Female | 7 | 70 | |
| Marital status | Single | 8 | 80 |
| Married | 2 | 20 | |
| Self-declared ethnicity | White | 8 | 80 |
| Mixed | 1 | 10 | |
| Indigenous | 1 | 10 | |
| Semester | 7th | 4 | 40 |
| 8th | 1 | 10 | |
| 9th | 3 | 30 | |
| 10th | 1 | 10 | |
| 12th | 1 | 10 |
MOTIVATION AND ENGAGEMENT
Students were primarily motivated by the pursuit of a transformative practical experience and a desire to serve vulnerable populations. Words such as vocation, empathy, and calling were frequently mentioned. One participant explained: "I joined the mission because I wanted to experience medicine beyond the classroom and serve those who are usually forgotten".
PRACTICAL AND EMOTIONAL CHALLENGES
Reported challenges included scarcity of basic supplies, long boat journeys, intense heat, lack of electricity, and limited communication with local residents. Emotionally, students described feelings of powerlessness in complex clinical scenarios and psychological strain when witnessing extreme deprivation. As one student stated: "We often felt powerless in the face of situations we could not fully solve". Another reflected: "The hardest part was realizing how much climate and geography define people's health and access to care".
EDUCATIONAL IMPACT AND PERSONAL TRANSFORMATION
All participants stated that the mission profoundly influenced their academic training and perception of medicine's social role. Frequently chosen words to describe the mission included intense, transformative, empathy, reality, and learning. As one student expressed: "The mission changed the way I see medicine and my responsibility toward vulnerable people".
As shown in Table 2, empathy was the most frequently cited word, followed by transformative and reality. This distribution indicates that the experience was perceived not only as a technical exercise but also as a deeply human and emotional encounter. The predominance of terms such as empathy and transformation reinforces the mission's role in shaping students' professional identity toward socially engaged and compassionate medical practice.
DISCUSSION
Participation in Amazon missions represents a deeply educational experience, integrating cognitive, emotional, and social dimensions of medical learning. The findings echo previous studies showing that experiential education promotes technical competence alongside empathy, resilience, teamwork, and ethical commitment11,12. Intrinsic motivation associated with serving underserved communities emerges as a central component in building a socially engaged medical identity and may act as a protective factor against burnout during training7. Logistical and emotional hardships serve as formative elements that accelerate professional maturity. Exposure to uncertainty and resource scarcity enhances decision-making skills and resilience, supporting Thompson et al.'s conclusions6 regarding the formative value of adversity in medical education. Furthermore, the subjective impacts reported by students, such as re-evaluating the physician's role and reaffirming vocation, corroborate evidence that humanizing experiences broaden critical awareness of health inequities and reinforce ethical commitment13.
These results align with other studies conducted in Amazonian contexts, where riverside, Indigenous, and quilombola populations face structural barriers to healthcare access, long travel distances, and seasonal isolation. Research on renewable energy alternatives for riverside communities, for instance, underscores how infrastructural fragility exacerbates health vulnerability while proposing innovative approaches to sustainability and equity14. Similarly, participatory and culturally adapted health education initiatives implemented in Amazonian communities demonstrate that humanized strategies can substantially enhance health promotion and strengthen community trust in medical teams15.
Beyond the Amazon, parallels can be drawn with international humanitarian experiences. Analyses of the Haitian context illustrate how poverty, fragile governance, and entrenched social inequities hinder effective health responses, echoing the systemic challenges found in remote Amazonian territories16. Moreover, Oliveira17 highlights the need to deconstruct Eurocentrism within humanitarian organizations such as Médecins Sans Frontières (MSF), emphasizing the importance of recognizing local agency and cultural perspectives. This critical reflection is equally relevant for Amazon missions, where respect for sociocultural diversity and the inclusion of community voices are essential to ethical medical practice.
Taken together, these comparisons reinforce the ethical dimension of medical education in vulnerable territories. Missions compel students to improvise under resource scarcity, confront dilemmas of distributive justice, and engage directly with communities often excluded from systemic care. Such challenges mirror those observed in short-term global health missions in crisis settings, where the tension between urgent needs and limited resources fosters critical reflection on the physician's role. By situating the Amazon experience within this broader humanitarian landscape, it becomes evident that these missions not only contribute to community health but also shape future physicians into professionals who are more resilient, socially conscious, and prepared for complex global health scenarios. Overall, the findings highlight the dual role of Amazon missions as both community service and transformative education, bridging local realities with global health debates.
CONCLUSION
The Amazon Volunteer Mission proved to be a transformative formative experience that strengthened both clinical and human competencies, including empathy, resilience, and social awareness. Immersion in vulnerable settings broadened students' understanding of health inequities and reinforced their commitment to ethical and socially engaged medical practice. Institutional support for such initiatives is recommended, as they contribute substantially to comprehensive physician training aligned with Brazil's real-world needs. By integrating socio-environmental determinants into medical education, these missions not only promote community health but also prepare future physicians to confront ethical and professional challenges in vulnerable contexts worldwide.

